

CCM without the hiring
Outsourced chronic care management
Companian staffs the monthly calls and time logs. You bill Medicare, and the codes pay the same as in-house.
- No new hires. We run outreach, consent and monthly calls.
- One file a month. Nothing is billed until you approve it.
- $0 upfront. Works with your EHR, live in about a week.
$66.13* per patient, every month*CPT 99490, 2026 national rate. We staff it.
Get your CCM Plan
Works nationwide
Practices nationwide
You bill under your own NPI
Same Care Advocate every month
RNs, NPs, LCSWs and care companions
Monthly file approved by your team
No new hires needed

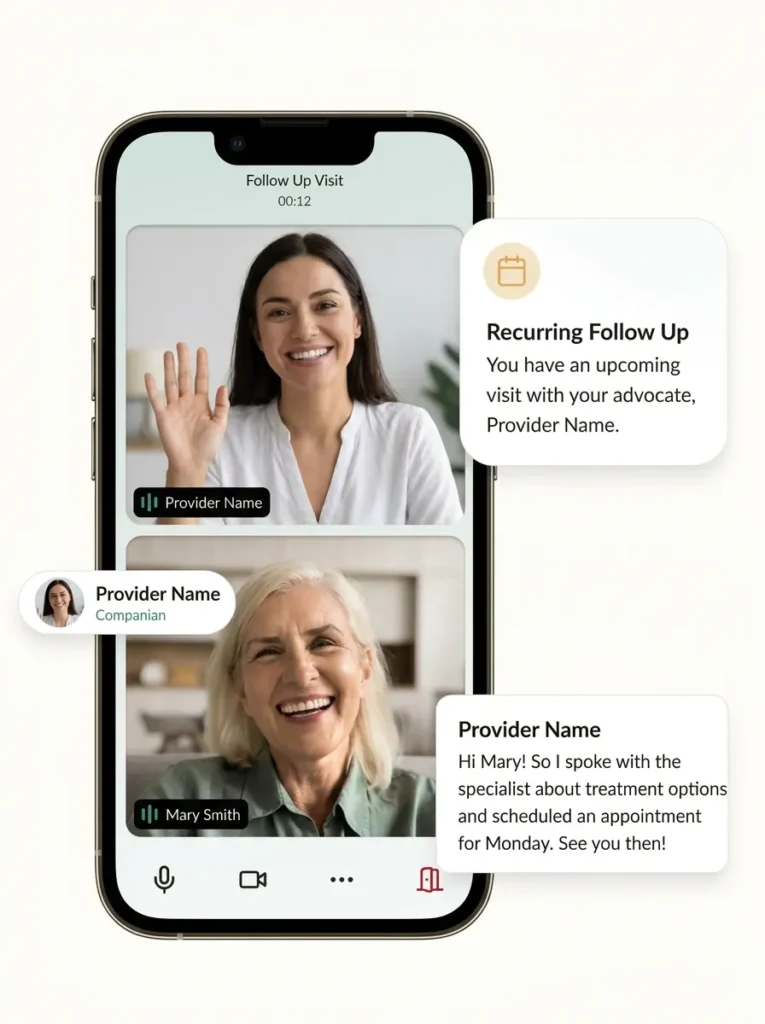

One Care AdvocateSame person, every month
Your NPI, your claimYou bill Medicare directly
Monthly billing fileYour team approves it
No upfront cost to the practice. Your team refers, we handle enrollment, outreach and documentation, and you bill Medicare under your own license. We connect with your EHR in about one week, and have worked with eClinicalWorks, Tebra and athenahealth.
In-house, software or outsourced CCM
Same CMS rules and the same codes. Different people doing the work.
| Question | Hire in-house | Software only | Outsource to a staffed service |
|---|---|---|---|
| Who calls patients each month | Your nurse or medical assistant | Your staff, inside the partner’s tool | The partner’s care team; at Companian, one Care Advocate per patient |
| Who enrolls patients and documents consent | Your staff | Your staff, with prompts from the tool | The care team, after you approve outreach |
| Who tracks the 20 minutes for 99490 | Your staff, by hand or in the EHR | A software timer, run by your staff | The care team, in a monthly file your billing team approves |
| Who hires and trains the people | You | You | An outsourced partner |
| What has to happen before the first claim | A hire, training and a time-tracking method | Setup, configuration and staff training | A services agreement, your patient list and outreach approval |
| Who keeps the care plan and clinical decisions | Your practitioner | Your practitioner | Your practitioner |
| Who bills Medicare | Your practice | Your practice | Your practice |
When hiring in-house fits
You already have a nurse or care manager with room on their panel and time for outreach, consent calls and the monthly time log. Salary and benefits run whether ten patients enroll or two hundred.
When software alone fits
Your staff has the hours but no way to time and document calls. A platform adds timers, templates and reports, not people.
When CCM outsourcing fits
Nobody on staff has time to call eligible patients every month. Your practitioner keeps referral, the care plan and the file sign-off. A hybrid works too: your coordinator keeps current patients, the outside team takes the rest. Our breakdown of in-house vs outsourced CCM weighs each model.
When outsourcing is the wrong fit
- Your patients already get CCM from another practitioner. Only one practitioner can bill CCM per patient per month.
- Your panel is largely ESRD patients billed under 90951 to 90970, which cannot be combined with CCM in the same period.
What 200 CCM patients bring in each month
2026 Medicare-allowed amounts, and the diagnosis codes that qualify.

Example panel
$13,226 / month
$158,712 a year · 200 patients × $66.13 (CPT 99490, national)
- CPT 99490 pays $66.13 per patient-month nationally (2026).
- Your locality moves it up or down: $60.71 in Arkansas to $83.76 in Alaska.
- Each extra 20 minutes adds CPT 99439 at $50.44.
| Condition | ICD-10 examples | Program fit |
|---|---|---|
| Hypertension | I10 | CCM with a second condition |
| Type 2 diabetes | E11.9 | CCM with a second condition |
| COPD | J44.9 | CCM with a second condition |
| CKD stage 3 | N18.31 | CCM with a second condition |
Can chronic care management be outsourced?
Yes, within the supervision rules CMS sets for the billing practitioner.
General supervision
CMS lets clinical staff furnish CCM incident to the billing practitioner under general supervision: the practitioner’s overall direction and control.
What stays with the billing practitioner
The initiating visit if required, the comprehensive care plan, every clinical decision and the claim. Outsourcing moves the work, not the responsibility.
The services agreement
It sets how your practitioner directs the care team and how documentation reaches your chart. Have your counsel confirm it meets incident-to rules.
Source: CMS MLN909188, Chronic Care Management Services. Nothing on this page is legal advice.
All CMS billing conditions, including 24/7 access, are in chronic care management requirements.

Who bills Medicare and who is paid
The claim stays yours. Only your cost to earn it changes.

| Money question | Hire in-house | Software only | Outsourced (Companian) |
|---|---|---|---|
| Who submits the Medicare claim | Your practice | Your practice | Your practice, under its own NPI |
| Who receives the Medicare payment | Your practice | Your practice | Your practice; Companian never bills Medicare |
| Who collects the patient’s Part B cost-sharing | Your practice | Your practice | Your practice |
| What your practice pays for | Salary, benefits, payroll taxes, recruiting and training | A software license and setup, plus your staff time | The fee in your services agreement, walked through on the intro call |
| Who is doing the work you pay for | Your employees | Your employees | Registered nurses, nurse practitioners, licensed clinical social workers and care companions |
What a CCM month is worth, whichever model you pick
For CPT 99490, Medicare pays $66.13 per patient-month nationally in 2026, before the patient’s share; your locality moves it up or down. See what chronic care management costs by code and locality.
Panel-size scenarios, including the add-on codes, are in the CCM reimbursement guide.
Fee structures to compare in writing
Staffed services charge per enrolled patient, by documented time, or as a share of collections. Have your counsel review how any partner is paid before you sign. A fuller checklist is in how to choose a chronic care management company.
Questions to ask any partner before signing
- Who makes the calls: your employees, contractors or software?
- Does each patient keep the same person every month?
- Who documents consent, and what does the patient hear about cost-sharing?
- What reaches our billing team at month end, field by field?
- How does our practitioner direct and supervise your team under the agreement?
- What happens to our patients and records if the agreement ends?
How outsourced chronic care management runs
Three touchpoints for your staff: the list, the outreach approval and the month-end file.

Agreement and list
Sign the agreement; share patients by EHR or referral form. Anyone new or unseen in a year needs an initiating visit.
Outreach and consent
You approve outreach once per patient. The Care Advocate explains cost-sharing and opt-out, then documents verbal consent.
The month
The same Care Advocate calls, asks care-plan questions and routes anything new to your clinicians. Gloria, our AI, drafts notes.
Month-end file
Minutes by activity, activities, codes and consent date per patient. You approve, then bill 99490, 99439, 99487 or 99489.
Questions about outsourced chronic care management

Do we lose control of our patients?
No. Referral is your choice patient by patient, and nothing reaches Medicare until your team approves the monthly file.
Is patient information protected?
Yes. Companian works under HIPAA and uses only the information needed to reach and document the patients you refer.
Can we outsource other care management programs too?
Yes: principal care management, principal illness navigation and community health integration run on the same model. APCM support is set up practice by practice.
How fast can we start?
Outreach begins once the agreement is signed, the list is shared and you approve the first patients. Then the pace follows your approvals.
Rates & disclosures
National amounts are 2026 Medicare Physician Fee Schedule non-facility payments at the non-QP conversion factor of $33.4009, computed from CMS RVUs. Your amount depends on your Medicare payment locality; see it in the CCM/PCM revenue calculator. Actual payment depends on participation status, place of service and cost-sharing.
Companian supplies Care Advocates and documentation to physician practices nationwide. Companian is not a medical practice and does not bill Medicare. The billing practitioner keeps the care plan, every clinical decision and the claim. Patients pay the usual Medicare Part B deductible and coinsurance for these services unless other coverage pays it.
Compare your in-house plan with a staffed service
Fifteen minutes with your patient mix and staffing costs. No patient information needed.