

Get paid between visits
Chronic care management for pulmonology practices
Companian checks in with your COPD and asthma patients every month, and flags flare signs to your team.
- No new hires. We run outreach, consent and monthly calls.
- One file a month. Nothing is billed until you approve it.
- $0 upfront. Works with your EHR, live in about a week.
$66.13* per patient, every month*Pulmonology CCM, CPT 99490 (2026 national rate)
Get your CCM Plan
Works nationwide
Practices nationwide
You bill under your own NPI
Same Care Advocate every month
RNs, NPs, LCSWs and care companions
Monthly file approved by your team
No new hires needed

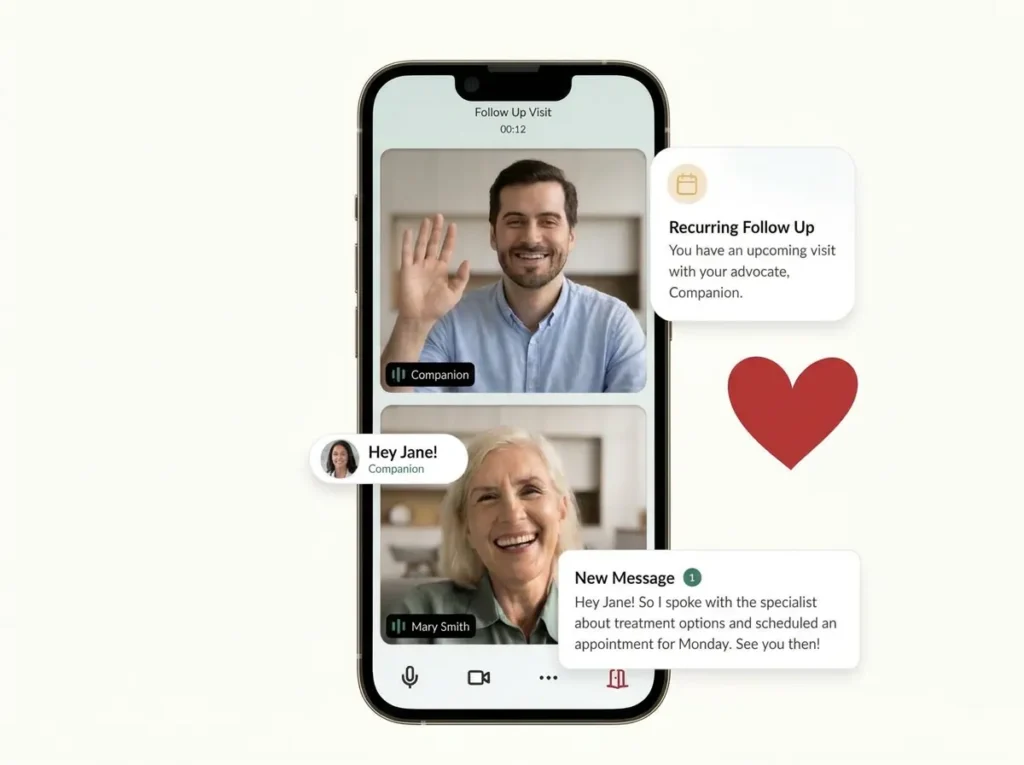

One Care AdvocateSame person, every month
Your NPI, your claimYou bill Medicare directly
Monthly billing fileYour team approves it
What a Care Advocate tracks for lung patients
Your action plans and thresholds set the script.
COPD
If you give patients an action plan, the Care Advocate asks about its warning signs and rescue inhaler use and flags changes to you.
Interstitial lung disease
Oxygen supplier contacts, pulmonary rehab attendance and reported side effects are recorded. Oxygen and antifibrotic decisions stay with your clinicians.
Severe asthma
Controller adherence questions are asked as your plan words them, and biologic injection appointments are confirmed ahead of time.
Sleep apnea
Questions about CPAP use, mask fit or equipment problems are routed to your practice or to the supplier, as your plan directs.

What 140 COPD, asthma and ILD patients bring in each month
2026 Medicare-allowed amounts, and the diagnosis codes that qualify.

Example panel
$9,258 / month
$111,098 a year · 140 patients × $66.13 (CPT 99490, national)
- CPT 99490 pays $66.13 per patient-month nationally (2026).
- Your locality moves it up or down: $60.71 in Arkansas to $83.76 in Alaska.
- Each extra 20 minutes adds CPT 99439 at $50.44.
| Condition | ICD-10 examples | Program fit |
|---|---|---|
| COPD | J44.9 | CCM with a second condition; PCM alone |
| Moderate persistent asthma | J45.40 | CCM with a second condition |
| Interstitial lung disease | J84.10 | CCM; PCM alone |
| Obstructive sleep apnea | G47.33 | CCM with a second condition |
Pulmonology PCM, CCM or PIN: picking the program
The number of conditions you manage, and the disease stage, decide it.
| Patient | Program | Codes | Rule that decides it |
|---|---|---|---|
| COPD is the one condition your practice manages | PCM (pulmonology principal care management) | 99426, 99427 for staff; 99424, 99425 for the pulmonologist | A serious, high-risk condition expected to last at least 3 months, with at least 30 minutes in the month |
| Your practice manages COPD and sleep apnea | CCM (pulmonology CCM) | 99490, 99439 | Two or more chronic conditions lasting at least 12 months with significant risk; one CCM practitioner per month |
| Advancing interstitial lung disease with evaluations and rehab to coordinate | PIN | G0023, G0024 | An initiating E/M visit (not 99211), staff trained on the condition, consent before services start and annually after |
| Patient moves to home health or hospice | No CCM that period | G0181, G0182 billed instead | CMS bars CCM in the same period as home health or hospice supervision |
| Code | Service | National 2026 |
|---|---|---|
| 99426 | PCM, clinical staff, first 30 min | $67.80 |
| 99424 | PCM, physician or QHP personally, first 30 min | $87.51 |
| 99490 | CCM, clinical staff, first 20 min | $66.13 |
| G0023 | PIN, first 60 min | $87.18 |
| G0024 | PIN, each additional 30 min | $54.44 |
Severe asthma works the same way: PCM alone, CCM alongside COPD or sleep apnea. Our PIN codes guide covers G0023 and G0024 in detail.
Chronic care management for pulmonology practices, step by step
Three sign-offs from your team, and monthly calls from ours.
Send the patient list
Use EHR access or a short referral form. Start with the COPD, ILD, asthma or sleep apnea patients you choose.
Approve outreach
The first call explains the program, Part B cost-sharing and how to stop. Verbal consent is recorded. Your staff can review what chronic care management is before outreach begins.
Calls through the year
One Care Advocate stays with each patient, asks about action-plan symptoms and confirms rehab sessions and injection visits.
Approve the monthly file
The file shows patient reference, program and code family, month of service, minutes by activity, activities and consent date.
CMS rules for lung disease care management
Monitoring codes, hurricane season and locality pay.
Remote monitoring
Chronic care management for pulmonology practices can sit beside RPM or remote therapeutic monitoring: CMS allows either one with CCM, but not both. In 2026 the RPM supply code splits by days of readings: 99445 for 2 to 15, 99454 for 16 to 30.
Hurricane season
If your care plan covers storm preparation, the Care Advocate asks those questions before a storm, such as whether oxygen users have the supplier’s number.
Pulmonary rehab and transport
If a ride keeps a patient from rehab, CHI codes G0019 and G0022 may apply after an initiating visit. No minute counts twice. See community health integration.
Pay by Medicare locality
Medicare pays by payment locality, set by state and county: 109 localities nationwide. For CPT 99490 the 2026 amount runs from $60.71 in Arkansas to $83.76 in Alaska. See CCM reimbursement by locality.
Questions pulmonology practices ask

What prompts a message to our clinicians?
Anything your action plan or care plan lists: more rescue inhaler use, more breathlessness, a missed rehab week, a new medicine from another doctor. It is recorded and routed under your escalation rules.
Does consent need renewing every year?
For CCM, no. Consent is documented once and stands until the patient stops. PIN consent comes before services begin and again each year. See CCM consent.
Who calls the patient, and how?
Remote registered nurses, nurse practitioners, licensed clinical social workers and care companions, by phone or video. Each patient always reaches the same Care Advocate. Gloria, an AI assistant, drafts documentation and pre-visit summaries; people make the calls.
Who supervises the care team?
The billing pulmonologist or NPP. CMS permits clinical staff to deliver care management under general supervision, set out in your services agreement. Confirm the arrangement with counsel.
How does Companian get paid?
Through a fee agreed with your practice, which we explain on the intro call. The Medicare payment goes to your practice under its NPI.
Rates & disclosures
National amounts are 2026 Medicare Physician Fee Schedule non-facility payments at the non-QP conversion factor of $33.4009, computed from CMS RVUs. Your amount depends on your Medicare payment locality; see it in the CCM/PCM revenue calculator. Actual payment depends on participation status, place of service and cost-sharing.
Companian supplies Care Advocates and documentation to physician practices nationwide. Companian is not a medical practice and does not bill Medicare. The billing practitioner keeps the care plan, every clinical decision and the claim. Patients pay the usual Medicare Part B deductible and coinsurance for these services unless other coverage pays it.
Care management for other specialty practices
Care Advocates work the same way in each specialty, around its conditions.
Add care management to your pulmonology practice
A 15-minute call about your COPD and ILD patients. No patient data needed.